Is Composite Bonding Painful? What You Need to Know
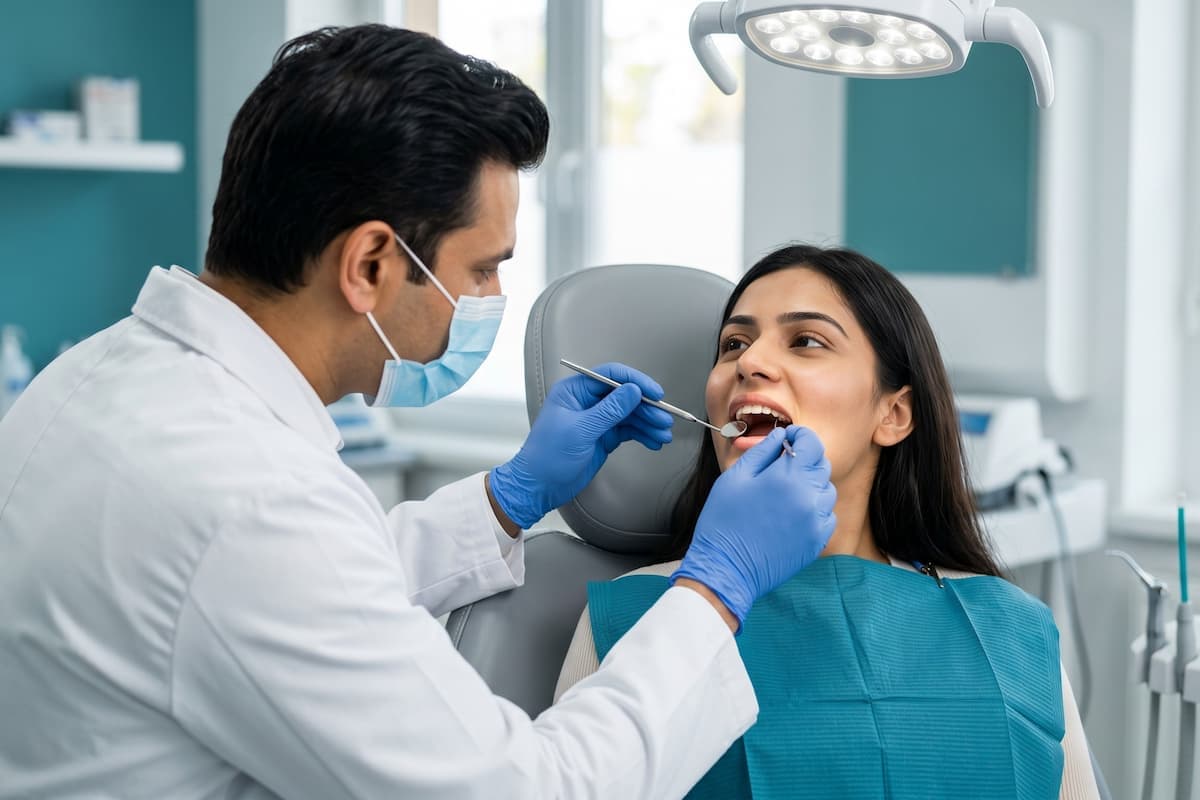
Composite bonding is widely perceived as one of the gentler cosmetic dental treatments, but "painful or not" is still a valid question. Patient experience depends on tooth condition, treatment scope, anxiety level, and whether any enamel or dentine preparation is required.
The short clinical answer is that severe pain is uncommon, but temporary sensitivity, pressure sensations, and occasional post-treatment tenderness can occur. Understanding when these sensations are expected, and when they are not, helps patients plan treatment more confidently.
Why composite bonding is usually well tolerated
Composite bonding is minimally invasive compared with many indirect restorations. In straightforward cases, the dentist can:
• prepare the surface conservatively,
• avoid deep drilling,
• preserve most natural tooth structure,
• complete treatment in one visit.
That conservative approach explains why many people describe bonding as "uncomfortable at times" rather than painful. For a baseline procedural overview, the composite bonding treatment page is useful before consultation.
What discomfort usually feels like during treatment
Most patients do not report sharp, escalating pain during bonding. Common sensations are:
• pressure while shaping and contouring,
• vibration from polishing instruments,
• cool-air or water sensitivity during isolation and finishing,
• mild jaw fatigue if multiple teeth are treated in one session.
These sensations can be more noticeable in anxious patients, in cases requiring edge lengthening, or where pre-existing sensitivity already exists.
Local anaesthetic: when it is used
Anaesthetic is often optional for small cosmetic refinements. However, clinicians may recommend it when:
• there is exposed dentine,
• existing cracks or wear facets increase sensitivity risk,
• bite adjustment is likely to be extensive,
• the patient has low pain tolerance or high procedural anxiety.
Choosing anaesthetic is not a sign something is wrong; it is a comfort-planning decision.
Clinical factors that increase the chance of sensitivity
Not all teeth respond the same way. Post-bonding tenderness is more likely when one or more of the following are present:
• enamel thinning from erosion or attrition,
• exposed cervical dentine,
• active or recent gingival inflammation,
• existing crack lines,
• high occlusal contacts after restoration placement.
This is why pre-treatment stabilisation matters. Optimising plaque control and soft-tissue health through targeted dental hygiene care often reduces procedural sensitivity and improves bonding conditions.
1) Examination and shade planning
Usually very comfortable. Some patients with sensitive teeth notice brief response during air-drying and photographic retraction.
2) Surface preparation
Often minimal. If roughening or contour changes extend near sensitive dentine, short-lived discomfort can occur.
3) Etching and bonding protocol
Generally well tolerated, but open dentinal tubules can increase transient cold sensitivity.
4) Composite placement and sculpting
Typically comfortable; pressure sensations are common.
5) Finishing and polishing
Minor sensitivity can occur during contour refinement, especially on thin incisal edges.
6) Occlusal adjustment
If bite points are high, adjustment may feel tender until contacts are balanced.
What is normal after bonding, and for how long
Mild sensitivity to temperature or pressure for a short period is common and often self-limiting. Typical post-treatment pattern:
• First 24 hours: awareness of treated surfaces and slight bite tenderness.
• Days 2-5: sensitivity usually decreases noticeably.
• By 1-2 weeks: most uncomplicated cases feel stable and comfortable.
What helps recovery:
• avoid very hard foods initially,
• chew more gently on newly treated teeth,
• use a soft brush and non-abrasive toothpaste,
• reduce thermal extremes for a few days.
Signs discomfort may not be routine
Seek review sooner if you notice:
• pain that worsens rather than improves,
• sharp pain on biting in one specific spot,
• persistent throbbing discomfort,
• a rough or catching margin irritating tongue or lip,
• new sensitivity that appears after initial improvement.
These signs may indicate high occlusion, marginal defect, crack progression, or another underlying issue that needs adjustment.
The bite factor: a common cause of "painful bonding"
Many reports of painful bonding are actually reports of unbalanced bite contacts. If a bonded edge takes excessive force during closure or chewing, teeth can feel bruised or sharp on pressure.
This is usually manageable with prompt occlusal adjustment, but delay can prolong symptoms and increase restoration stress.
Good clinicians therefore treat bite verification as essential, not optional:
• static closure checks,
• excursion checks,
• selective polishing and re-checks,
• patient feedback after first functional days.
Managing anxiety-related pain amplification
Pain experience is not only structural; it is also perceptual. Patients with high treatment anxiety often perceive normal sensations as threatening, which amplifies discomfort.
Useful strategies include:
• discussing each step before starting,
• agreeing hand signals for breaks,
• pacing longer appointments,
• using topical or local anaesthetic proactively where appropriate,
• scheduling follow-up reassurance checks.
This approach improves patient comfort and often reduces post-treatment symptom reporting.
Composite bonding versus other cosmetic pathways
Patients frequently compare bonding with whitening or veneers. Comfort is one part of that choice, but so are material behavior and longevity.
Bonding versus whitening
If colour is the main concern, exploring professional whitening options first may reduce the amount of additive composite required and improve shade planning.
For patients worried about bleaching discomfort, this whitening safety explainer helps set realistic expectations about sensitivity and risk control.
Bonding versus veneers
Bonding is typically more conservative and easier to repair chairside, but may stain or wear faster in high-demand cases. Veneers can offer superior long-term color stability and optical control at the cost of greater planning complexity.
If your goals involve substantial shape redesign or nuanced translucency control, the porcelain veneer investment guide gives a fuller framework for comparison.
How clinicians reduce pain risk in practice
Comfort-focused bonding protocols usually include:
• pre-op sensitivity screening,
• minimally invasive preparation design,
• moisture control and isolation discipline,
• incremental layering to reduce stress concentration,
• conservative finishing with heat/friction awareness,
• occlusal verification before discharge.
In higher-risk sensitivity cases, dentists may add:
• desensitising agents,
• selective anaesthesia,
• staged treatment rather than full-arch completion in one visit,
• earlier post-op review to fine-tune contacts.
Long-term comfort and maintenance
Comfort does not end at placement. Ongoing habits affect both symptoms and restoration life.
Key maintenance principles:
• use non-abrasive oral care products,
• avoid parafunctional habits such as nail biting or pen chewing,
• wear protective appliances if prescribed,
• attend periodic reviews and hygiene appointments,
• report chips early before edge defects worsen.
Small adjustments made early usually prevent bigger functional discomfort later.
Questions to ask at consultation
Before committing, consider asking:
• Do my teeth show signs of existing sensitivity risk?
• Will any part of treatment likely need anaesthetic?
• How many teeth are planned in one session?
• What post-op sensitivity should I expect in my case?
• How soon can bite adjustments be done if needed?
• What maintenance schedule is recommended for comfort and longevity?
These practical questions often provide better clarity than broad "Will it hurt?" discussions.
Practical preparation checklist for a smoother appointment
Comfort improves when patients arrive prepared. In the week before treatment, keep oral hygiene consistent, reduce inflammatory triggers like aggressive brushing, and let your clinician know about any recent sensitivity spikes. On the day, avoid rushing to the appointment, eat beforehand if advised, and communicate clearly about anxiety levels so pacing can be adjusted early rather than mid-procedure.
After bonding, follow the short-term guidance exactly even if symptoms are mild. Patients who ignore early bite awareness or postpone minor adjustments are more likely to describe treatment as painful later, even when the issue is simple to correct. A structured first review, especially for multi-tooth cases, is often the difference between a merely acceptable recovery and a genuinely comfortable one.
Finally, keep expectations specific: comfort is the goal, not zero sensation. Brief awareness during and after treatment can still be compatible with excellent outcomes, provided symptoms trend down and function remains stable.
Frequently Asked Questions
1. Is composite bonding painful without anaesthetic?
Many minor bonding procedures are tolerated without anaesthetic, but comfort depends on tooth sensitivity and treatment depth. Anaesthetic can be used whenever clinically helpful.
2. How long does sensitivity last after bonding?
Most mild sensitivity settles within days to a couple of weeks. Persistent or worsening pain should be reviewed.
3. Can bonding cause nerve damage?
Routine superficial bonding does not usually endanger pulp vitality. Risk is higher when teeth already have deep cracks, extensive wear, or prior pathology.
4. Is pain worse when multiple teeth are done together?
Not always, but jaw fatigue and post-op bite awareness may be more noticeable in longer sessions.
5. What if one bonded tooth hurts to bite?
That often suggests a high contact point and should be checked promptly for occlusal adjustment.
Conclusion
Composite bonding is usually a low-pain, high-control cosmetic treatment when diagnosis, technique, and bite adjustment are handled properly. Temporary sensitivity can occur, but severe pain is uncommon and should always be reviewed rather than ignored.
The best predictor of a comfortable experience is careful planning: stabilised oral health, realistic goals, conservative execution, and clear follow-up pathways.
Disclaimer
This article is for general educational information and is not a diagnosis or treatment plan. Individual suitability, risks, and outcomes vary and can only be confirmed after a clinical examination by a qualified dental professional. If you have symptoms or concerns, seek personalised advice from your dentist.
Written Date: 12 October 2026 | Next Review Date: 12 October 2027
Written by Dr. Drina Popat · reviewed by Dr. Drina Popat
This article is general information, not personal clinical advice. For a diagnosis and a plan tailored to you, book a consultation with a GDC-registered dentist.
Related treatments at our Wimpole Street practice